The science behind ageing hair, thinning, greying and how to support hair vitality
Your hair has been ageing alongside you the whole time; it's just kept a low profile. If it feels finer or greyer than expected, that comes down to biology. Understand the mechanics, and you'll know what's fixed, what's flexible, and where effort actually pays off. You can't stop the clock, but you can support your hair's longevity with the right care.
What is hair ageing, really?
Hair ageing isn't split ends or a bleach job gone wrong; that's mechanical damage to hair that’s already grown. It's about the quality of hair your follicles are producing, and how long that lasts.
Hair ageing = physiological + environmental factors
+ Physiological: genetics (family history), hormones, inflammation, follicle stem cell activity
+ Environmental: UV exposure, lifestyle, colouring, chemical processing, stress, smoking, diet 16, 21
Think of hair ageing as an umbrella term: a few overlapping processes, rather than one neat condition, and there is still plenty being learned about how they interact 21.
What causes hair thinning? Follicle miniaturisation explained
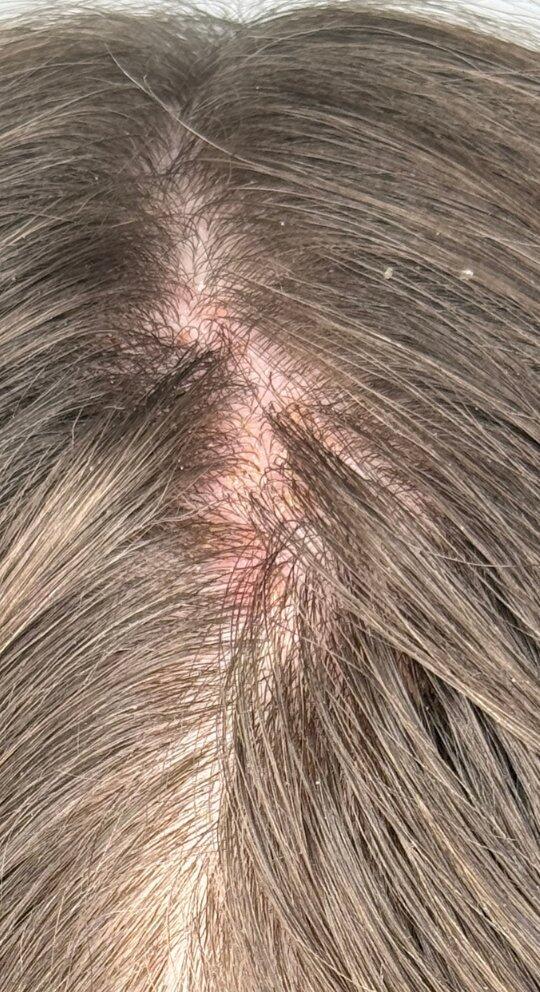
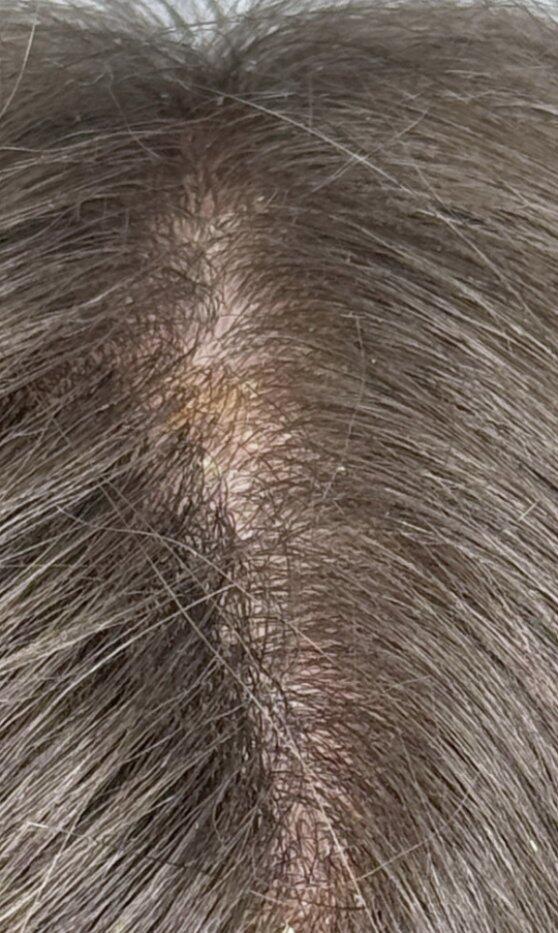
In androgenetic alopecia (AGA), hairs from affected follicles become progressively smaller, shorter, and lighter until the follicle shrinks completely and stops producing hair in both sexes 28, 29. Like a factory slowly downsizing output until it closes.

DHT (a byproduct of testosterone) drives this, binding to the androgen receptor in susceptible follicles and switching on genes that shrink them. Back-of-head follicles largely dodge this, which is why transplants from that area last 21.
Note: Follicle miniaturisation is specific to androgenetic alopecia (AGA). Other forms of thinning (telogen effluvium, nutritional shedding, thyroid-related thinning) work differently and are covered later in this blog.
Why does hair go grey?
Melanin, made by melanocytes, gives hair its colour. As melanocytes age, they produce less melanin, reflecting reduced stem cell activity, not fewer cells 16.

As you age, your hair follicles naturally start producing hydrogen peroxide, the same stuff you'd use to bleach hair at a salon! Over time, it builds up right inside the hair shaft itself, in very small amounts.
Normally, your body has a built-in defence against this, an enzyme called catalase. Catalase breaks hydrogen peroxide down; however, as we age, our natural catalase levels drop, and hydrogen peroxide builds up instead of being cleared.
Leftover peroxide doesn't just sit there; it actively damages tyrosinase, the enzyme your hair needs to produce colour in the first place. This peroxide contributes to the bleaching of your hair from the inside. Peroxide causes a specific kind of oxidative damage to the tyrosinase enzyme that limits its ability to function, which drives the gradual loss of hair colour. So it's genuinely a double hit. Less cleanup of the peroxide, and the peroxide itself sabotaging the pigment-making machinery.
UV exposure accelerates greying. UVB and UVA absorbed by hair release free radicals that damage protein structure. Melanin normally mops these up, but excess free radicals degrade melanin itself, meaning less pigment and less UV protection16. This creates a feedback loop that speeds up colour loss. Grey hair, with less melanin, is especially vulnerable to sun degradation. Separately, UV that reaches the scalp can also damage the follicle directly, actively contributing to oxidative stress and potentially accelerating greying.
Why does hair get thinner?

Thickness shifts too:
+ Women’s hair thickness peaks around 40 years old; 38% of women over 50 show significant thinning 13, 25
+ Men's thickness often declines from ~30 years old 13, 25
Structural properties (stretch, bend, twist) and lipid composition shift with age; texture drifts as follicle shape changes, worsened by chemical/environmental exposure 21. Less sebum changes how hair feels 21. Stem cell activity declines, making regeneration harder 26.
Is hair loss genetic, or is it lifestyle?
+ Internal factors: genetics, epigenetics, androgenetic alopecia, early greying, senescent alopecia (after 60)
+ External factors: UV, smoking, nutrition, lifestyle, pollution 21, 26
A review of 31 studies found that high insulin, smoking, poor sleep, alcohol and high blood pressure all accelerate the progression of hair loss15. Genetics has a much stronger influence than lifestyle:
+ A family history of hair loss increases the odds by 2.72 times and the odds of progression by 4.24 times
+ Smoking increases the odds by 1.46 times and the odds of progression by 1.60 times
+ Overall, genetics roughly quadruples the risk, while smoking increases it by around 50% 15
UV damages both colour and structure. Beyond greying, UVB and UVA exposure releases free radicals that damage the protein structure of hair itself 16. Heat styling, scalp inflammation, poor sleep, alcohol, and high-sugar diets add to scalp ageing 15, 19.
Is hair loss different in men and women?

Yes, but the basics are the same. In both sexes, hair follicles at the front of the scalp are more sensitive to DHT (dihydrotestosterone, a potent form of testosterone that shrinks follicles). In contrast, follicles at the back convert androgens into oestrogen more effectively, which is protective. Both male and female pattern hair loss run in families and involve multiple genes 16, 21.
The key difference? Women's follicles are naturally less reactive to DHT. A landmark biopsy study by Sawaya and Price found women have around 40% fewer androgen receptors, about 6 times more aromatase (the enzyme that converts androgens to oestrogen), and 3 to 3.5 times lower 5α-reductase (the enzyme that makes DHT) 30.
This likely explains why women tend to have milder hair loss, keep their hairlines longer, and why finasteride (which blocks DHT production) works less reliably in women than in men 30.
To learn more about the different types of hair loss in men and women, explore our guides to female hair loss and male hair loss.
Does menopause cause hair loss, and does testosterone cause it in men?
Women:
+ Telogen effluvium and frontal fibrosing alopecia both become more common after menopause 27
+ Oestrogen falls faster than androgens, shifting the balance so androgens have relatively more influence even though levels don't rise — which is why Female Pattern Hair Loss (FPHL) can worsen without any actual androgen increase 27
+ Most women with FPHL have normal androgen levels; it's the oestrogen drop that's doing the damage, which is why "androgenetic alopecia" is being retired as a term for women 27
+ Postmenopausal women tend to have fewer hairs in the growth phase, thinner strands, slower growth rates and possibly reduced blood supply to follicles 16, 27
+ The hormonal transition can start up to 10 years before periods stop (average menopause age is 51) 27
+ Onset is typically in the 50s-60s, occasionally 30s-40s; it's common, increases with age, varies by ethnicity and is most common after menopause 28, 32
Men:
+ There's no clear mechanism linking male pattern baldness to falling testosterone; DHT stays steady even as testosterone declines17
+ The Massachusetts Male Aging Study (1,709 men, aged 40-70) found testosterone fell about 1.6% per year, bioavailable testosterone 2-3% per year, DHEA/cortisol/oestrone all fell, but DHT actually rose 17
+ Most DHT comes from conversion in peripheral tissues, not the testes, so it doesn't track gonadal decline; lower testosterone offers no protection — older men have simply had longer for the process to unfold 17
+ There's no male equivalent of the menopause research; men in good health showed 10-15% higher androgens, suggesting poor health accelerates androgen decline 17
What are the main drivers of hair ageing?
Four main processes come together to drive hair ageing:
+ Androgen-driven miniaturisation (AGA/FPHL)
+ Chronological follicle ageing (stem cell decline)
+ Melanocyte ageing (greying)
+ Endocrine or systemic shifts (menopause, thyroid, cortisol)
These processes converge around oxidative stress, melanocyte loss, stem cell decline, and external factors like UV, smoking and pollution that speed things up 21.
Is menopausal hair loss the same as male pattern baldness?
The presentation is similar (patterned thinning), but women's frontal hairline is usually spared thanks to higher local aromatase (the enzyme that converts androgens to oestrogen) 28,30. For both sexes, progression is very slow (years to decades), and earlier onset can mean faster progression28, 29. For men, later-life loss is a continuation of the same process. There's debate about whether independent stem cell decline drives diffuse thinning after 60 ("senescent alopecia"), though most presumed cases turned out to be regular pattern loss 21. Women get a distinct hormonal chapter; men get more of the same story, further along.
Can thyroid problems cause hair loss?
Thyroid problems are more common in women from their 40s onwards, and hair follicles respond directly to thyroid hormone changes 18. When thyroid hormone is low, the growth phase shortens and shedding increases; thyroid hormone helps extend the growth phase and reduces cell death in follicles while supporting pigment production 18. Hypothyroidism (underactive thyroid) typically causes brittle, dry hair with diffuse shedding. Hyperthyroidism (overactive thyroid) can make hair finer, softer and silkier, also with diffuse shedding that may come on quickly.
Both types can coexist with pattern loss, but the key difference is that thyroid-related shedding is fully reversible once treated 18.
Can stress actually cause hair loss?
Hair follicles have their own stress-response system, similar to the body's main stress pathway 22. When you're stressed, this system releases signals that tell your adrenal glands to produce cortisol, which can inhibit hair growth and push follicles into an early resting phase 22. This typically shows up as diffuse shedding (telogen effluvium), appearing two to three months after the stressful event 22. Stress is linked to telogen effluvium, androgenetic alopecia and alopecia areata, and the relationship goes both ways (hair loss causes distress, which can worsen the condition) 22. It's worth noting that this mechanism research is currently lab-based only.
Is my hair loss normal ageing, or is it moving too fast?
On schedule (late 30s-50s):
+ Density declines gradually from 35 (peak 20s-30s)
+ Diameter peaks at ~40 in women
+ Texture shifts from follicle shape change and less sebum
+ Progression is slow, years to decades 13,14, 16, 21, 28, 29
Factors that can speed up hair loss:
+ Earlier onset (may mean faster progression) 28, 29
+ Rapid change (pattern loss is slow by definition)
+ Smoking 15
+ High insulin, poor sleep, alcohol, high blood pressure 15
+ Excessive UV exposure (solar elastosis precedes AGA) 21
+ Chronic stress load 22
+ Crash dieting
+ Family history of early-onset loss 28, 29
What else can cause hair thinning besides ageing?
Thyroid problems: diffuse shedding, brittle or dry hair, fully reversible once treated 18
Iron/ferritin: a genuine causative factor. In 18 women with iron deficiency but no anaemia, hair loss stopped with oral iron and resumed when paused 40. Standard labs start at 12-15 ng/mL; healthy-hair level is 50-70 ng/mL 40
Vitamin D: deficiency is common across hair loss types (50.4% FPHL, 47.4% male AGA, 53.5% telogen effluvium, 51.9% alopecia areata); receptors are present in the follicle39. Iron deficiency is more common in premenopausal women, vegans and vegetarians, and bariatric surgery patients (roughly 2-5% of men and postmenopausal women); vitamin D deficiency is similar across types and sexes 40, 39
FPHL diagnosis is based on history and pattern, with the scalp typically looking normal; testing matters since thyroid, iron and perimenopausal FPHL can look similar 28 29.
What actually works for hair loss and thinning?
Minoxidil: the most effective topical monotherapy among FDA- and TGA-approved treatments (33 studies, 19 comparators) 33, 34. Works independently of androgens, so it's effective in men over 60 and women regardless of oestrogen levels, including post-menopause 21. Needs at least 6 months before you'll see benefit, only lasts while you keep using it, and may cause an initial shed in weeks 4-6 28.
Finasteride: the best-evidenced treatment overall; 1mg/day slowed progression and increased growth over two years in men 23. Not licensed for women (unlicensed options include spironolactone, cyproterone acetate, flutamide and bicalutamide, with pregnancy and liver toxicity cautions) 28. Dutasteride 0.5mg/day ranked more effective than finasteride but is off-label for hair loss 34. Combinations beat monotherapy: finasteride plus minoxidil ranked highest for men (SUCRA 80.18%); microneedling plus minoxidil ranked highest for women (87.18%) 42.
Topical actives:
+ Caffeine: the best-evidenced individual active; a 24-week RCT in 154 men showed it inhibits phosphodiesterase, raises cyclic AMP and counters DHT at the follicle 37
+ Copper peptides (GHK-Cu): activate Wnt/β-catenin, raise VEGF and IGF-1, but evidence is very low-grade with no large trials and poor skin penetration without microneedling 38
+ Growth factors (IGF-1, FGF-7): still seen as experimental
+ Mane Event Elixir®: Hair growth serum formulated by trichologists, naturopaths and nutritionists that combines potent peptide boosters (Akosky Azuki™, Hairgenyl™) and bond-building FibreHance™ at clinically proven levels. Advanced liposomal technology drives actives 1.6x faster and 2.5x more effectively into the scalp compared to traditional delivery methods. Consumer data shows a 112.7% improvement in the growing-to-shedding ratio, an 88% increase in hair density, a 133% improvement in hair strength, and a 92% increase in scalp microcirculation*.
*Clinical study on key active ingredients.
UV and scalp protection: Protect bald or thinning areas with sunblock, a hat or a wig 28. Grey hair (with less melanin) is especially vulnerable to sun degradation 21.
Shampoo: Inflammatory scalp conditions like dandruff and seborrhoeic dermatitis contribute to oxidative stress 19, 21. Studies show 2% ketoconazole shampoo (with or without minoxidil) improved anagen follicle density even without dandruff 19. Zinc pyrithione plus minoxidil increased net hair counts 19. That said, the efficacy of actives in shampoo form is limited by dilution with water and short contact time unless they're formulated for absorption 21.
Nutrition: Hair longevity comes down to giving follicles what they need to stay active longer. Vitamin D can help with androgenetic alopecia (AGA) and telogen effluvium, and low iron should prompt supplementation plus a vitamin C level check to support absorption 20. Protein supplies the keratin that hair is made of, and B vitamins (including folate and B12) support the cellular energy follicles demand to keep growing. Omega-3 helps calm scalp inflammation, zinc and iodine support the hormones that regulate the growth cycle, iron carries oxygen and nutrients to follicle cells, and vitamin D, selenium and biotin support both follicle cycling and the keratin structure itself. Correcting deficiencies in iron, vitamin D, folate, B12 and selenium also shows some evidence for improving premature greying 20. When these basics are in place, follicles are better equipped to age well instead of dropping out of the growth phase early.
Lifestyle: quitting smoking removes a real contributing factor but won't reverse genetic pattern loss 15,16. Poor sleep, alcohol, high insulin and high blood pressure all showed an association with faster AGA progression15. For women in perimenopause, sun protection, stress management, good nutrition, weight management, regular exercise and quitting smoking early may help ease symptoms and reduce the risk of further hair decline before menopause 27. Improving general and nutritional health may help slow loss; there are cosmetic options for improving appearance, and medical treatments which, when used long-term, can improve hair growth 32.
Apotecari's approach: Apotecari formulates targeted hair and scalp treatments using clinically studied ingredients at doses that deliver. Expert-formulated by nutritionists, naturopaths, trichologists and scientists, the range addresses hair loss and thinning at multiple levels. Each formulation uses advanced delivery systems to ensure ingredients reach the follicle at effective concentrations, addressing hair loss and thinning with precision grounded in research.

The collection:
+ Mane Event®: 17 bioactive ingredients including dual amino acid complex, activated B vitamins, biotin, zinc, iron, silica and Hairtellectual® hyaluronic acid for intensive growth from within
+ Mane Event Elixir®: advanced hair growth serum powered by Akosky Azuki™, Hairgenyl™ and FibreHance™ at clinically proven levels, plus advanced liposomal technology that drives potent peptides and botanicals deep into the follicle — clinical studies showed 1.6x faster activity, 2.5x greater efficacy, 112.7% increase in the growing-to-shedding ratio, 133% improvement in hair strength, 88% increase in hair density and 92% increase in scalp microcirculation
+ Crowning Glory®: 11 bioactive ingredients including omega-3 and omega-6 fatty acids, vitamin D, zinc, selenium and Hairtellectual hyaluronic acid to reset scalp health and balance hydration
+ Hair Atelier®: 74% plant-sourced proteins from brown rice, sunflower and pea, plus a superfood blend with beetroot, baobab, bamboo and native Australian fruits to build strength and thickness
What doesn't work, despite being popular?
+ PRP (Platelet-rich Plasma): evidence is still too limited to say when or how it might work 28
+ Reversing chronological follicle ageing (stem cell quiescence, niche stiffening, melanocyte depletion): no proven human intervention yet; greying photoprotection research is mouse-only 26
+ Cosmetic treatments alone won't reverse the ageing process, though leave-on combinations with caffeine, niacinamide and panthenol can help reduce the visible effects of age-related thinning 21
Signs it's time to see someone:
Starting treatment earlier means you lose less hair, which gives you more to work with 31. That said, certain signs mean seeing a professional is particularly important. And if you're concerned in any way, there's never a bad time to seek guidance.
A few signs in particular are worth flagging, since they could point to something beyond typical pattern loss:
+ Scaling, crusting or pus-filled bumps can signal an infection that needs testing 36
+ Loss of visible follicle openings (the tiny pores where hairs grow) — this points to scarring alopecia, which permanently destroys follicles and is the most urgent reason to get checked 36
+ Rapid or patchy change, since pattern loss is usually slow and gradual 28, 29
+ Fatigue, unexplained weight change or feeling too hot or cold, which can suggest thyroid or autoimmune issues
+ Family history of early-onset hair loss 28, 29
For women, pattern hair loss plus acne, excess facial hair, irregular periods or trouble conceiving can point to PCOS/ PMOS 28. Frontal fibrosing alopecia (a scarring, permanent type that often starts after menopause) warrants checking for hairline changes 27.
For men, diagnosis needs a full history and scalp exam, occasionally blood tests 29. Men with diffuse loss deserve the same thyroid, ferritin and vitamin D workup women get — the male hormonal equivalent is real but under-researched.
Hair loss can take a toll on self-esteem and body image. Addressing the emotional impact with a professional is just as important as treating the physical side 28.
The bottom line
Hair ageing is real, driven by genetics, hormones, environment, and lifestyle. You can't stop the clock, but you can support your hair's longevity. Protect your scalp, manage stress and sleep, correct real deficiencies, and use evidence-backed treatments consistently. Quitting smoking helps. If something feels faster or patchier, get it checked; the earlier, the more options stay open.
Not sure where your hair sits on this timeline? Take the quiz for a personalised read on what's going on and which formulations suit your hair right now.

References
13. Otsuka H, Nemoto T. Study on Japanese hair. Koshokaishi. 1988;12:192–7. (As cited in Trüeb et al. [21].)
14. Robbins C, Mirmirani P, Messenger AG, Birch MP, Youngquist RS, Tamura M, et al. What women want — quantifying the perception of hair amount. Br J Dermatol. 2012;167:324–32. doi:10.1111/j.1365-2133.2012.11010.x
15. Li H, Li W, Zhang J, et al. Risk factors for androgenetic alopecia: a systematic review and meta-analysis. BMC Public Health. 2026;26:1000.
https://doi.org/10.1186/s12889-026-26258-y
16. Maymone MBC, Laughter M, Pollock S, Khan I, Marques T, Abdat R, Goldberg LJ, Vashi NA. Hair aging in different races and ethnicities. J Clin Aesthet Dermatol. 2021;14(1):38–44. https://pmc.ncbi.nlm.nih.gov/articles/PMC7869811/
17. Feldman HA, Longcope C, Derby CA, et al. Age trends in the level of serum testosterone and other hormones in middle-aged men: longitudinal results from the Massachusetts Male Aging Study. J Clin Endocrinol Metab. 2002;87(2):589–598. https://academic.oup.com/jcem/article/87/2/589/2846777
18. Van Beek N, Bodó E, Kromminga A, et al. Thyroid hormones directly alter human hair follicle functions. J Clin Endocrinol Metab. 2008;93(11):4381–4388.
19. Trüeb RM. Shampoos: composition and clinical applications. Int J Trichology. 2018. https://pmc.ncbi.nlm.nih.gov/articles/PMC6369642
20. Almohanna HM, Ahmed AA, Tsatalis JP, Tosti A. The role of vitamins and minerals in hair loss: a review. Dermatol Ther (Heidelb). 2019;9:51–70. https://doi.org/10.1007/s13555-018-0278-6
21. Trüeb RM, Rezende HD, Gavazzoni Dias MFR. A comment on the science of hair aging. Int J Trichology. 2018;10(6):245–254. doi:10.4103/ijt.ijt_56_18
22. Kim JE, Cho BK, Cho DH, Park HJ. The local hypothalamic–pituitary–adrenal axis in cultured human dermal papilla cells. BMC Mol Cell Biol. 2020. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7310274/
23. Kaufman KD, Olsen EA, Whiting D, et al. Finasteride in the treatment of men with androgenetic alopecia. J Am Acad Dermatol. 1998. https://pubmed.ncbi.nlm.nih.gov/9777765/
24. Alanazi et al. Evaluating the effectiveness of commercial oral supplements for hair growth: a systematic review and meta-analysis. J Cosmet Dermatol. 2026. https://onlinelibrary.wiley.com/doi/10.1111/jocd.70817
25. UCLA Health. Your guide to aging and hair. https://www.uclahealth.org/news/article/your-guide-aging-and-hair
26. Aging of hair follicle stem cells and their niches. https://pmc.ncbi.nlm.nih.gov/articles/PMC9887102/
27. Menopause and hair loss in women: exploring the hormonal transition. Maturitas. 2025. https://www.maturitas.org/article/S0378-5122(25)00186-0/fulltext
28. British Association of Dermatologists / British Hair and Nail Society. Hair loss — female pattern (androgenetic alopecia). Patient Information Leaflet. Produced June 2012, updated October 2024, next review October 2027. https://cdn.bad.org.uk/uploads/2021/11/25160409/Hair-loss-female-pattern-PIL-Oct-24.pdf
29. British Association of Dermatologists / British Hair and Nail Society. Hair loss — male pattern (androgenetic alopecia). Patient Information Leaflet. https://www.bad.org.uk/pils/hair-loss-male-pattern-androgenetic-alopecia
30. Sawaya ME, Price VH. Different levels of 5α-reductase type I and II, aromatase, and androgen receptor in hair follicles of women and men with androgenetic alopecia. J Invest Dermatol. 1997;109(3):296–300. https://pubmed.ncbi.nlm.nih.gov/9284093/
31. American Academy of Dermatology. Hair loss: diagnosis and treatment. https://www.aad.org/public/diseases/hair-loss/treatment/diagnosis-treat
32. Women's Health Concern (British Menopause Society). Menopausal hair loss - more than 'a bad hair day'. Factsheet, November 2025. https://www.womens-health-concern.org/wp-content/uploads/2025/11/16-NEW-WHC-FACTSHEET-MenopausalHairLoss-NOVx=2025-C.pdf
33. Gupta AK, Venkataraman M, Talukder M, Bamimore MA. Relative efficacy of minoxidil and the 5-α reductase inhibitors in androgenetic alopecia treatment of male patients: a network meta-analysis. JAMA Dermatol. 2022;158(3):266–274. https://pubmed.ncbi.nlm.nih.gov/35107565/
34. Gupta AK, Bamimore MA, Williams G, Talukder M. Comparative efficacy of minoxidil and 5-alpha reductase inhibitors monotherapy for male pattern hair loss: network meta-analysis. J Cosmet Dermatol. 2025;24(7):e70320. https://pmc.ncbi.nlm.nih.gov/articles/PMC12207719/
35. Adil A, Godwin M. The effectiveness of treatments for androgenetic alopecia: a systematic review and meta-analysis. J Am Acad Dermatol. 2017;77:136–141. (Cited by AAD [31].)
36. Approach to the patient with hair loss. J Am Acad Dermatol. 2023. https://www.jaad.org/article/S0190-9622(23)00979-9/fulltext
37. A novel approach against male pattern hair loss with topical dimethylglycine sodium salt and caffeine: 24-week double-blind randomised placebo-controlled trial. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12359291/
38. Peptides for hair regrowth: evidence and protocols, 2026. https://education.mirrorplasticsurgery.com/peptides/peptides-for-hair-regrowth-2026/
39. Vitamin D deficiency in non-scarring and scarring alopecias: a systematic review and meta-analysis. 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11479915/
40. Serum ferritin and vitamin D levels should be evaluated in patients with diffuse hair loss prior to treatment. https://pmc.ncbi.nlm.nih.gov/articles/PMC7394174/
41. Relative efficacy of minoxidil in combination with other treatments for androgenic alopecia: a network meta-analysis of RCTs. PROSPERO CRD42024623164. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12483851/